
Quickstart Highlights
KPV (Lys-Pro-Val) is the C-terminal tripeptide of alpha-melanocyte-stimulating hormone. It retains the anti-inflammatory activity of the parent hormone without its pigmentation effects and is studied in animal and cell models for intestinal inflammation, systemic inflammation and skin conditions. This educational protocol presents once-daily subcutaneous injections for a 4–8 week cycle, beginning at 200 mcg and moving to a 300 mcg working dose from week 3, with 500 mcg as the upper reference. A 2.0 mL reconstitution of the 10 mg vial gives 5 mg/mL, so each unit on a U-100 syringe delivers 50 mcg and every dose on this page falls on whole units.
- Reconstitute: Add 2 mL bacteriostatic water → 5 mg/mL concentration.
- Dose range: 200–500 mcg (0.2–0.5 mg) once daily, subcutaneously (4–8 week cycle, then 2–4 weeks off).
- Easy measuring: At 5 mg/mL, 1 unit = 0.01 mL = 50 mcg on a U-100 insulin syringe.
- Storage: Lyophilized: freeze at −20 °C (−4 °F); after reconstitution, refrigerate at 2–8 °C (35.6–46.4 °F) and use within 28 days.

Dosing & Reconstitution Guide
Standard Protocol (2 mL = 5 mg/mL)
| Week | Dose | Calculated volume | U-100 scale value (1 mL capacity) | V1 nominal setting (units) |
|---|---|---|---|---|
| Weeks 1–2 | 200 mcg (0.2 mg) | 0.04 mL | 4 units | 4 units |
| Week 3 onward | 300 mcg (0.3 mg) | 0.06 mL | 6 units | 6 units |
| Upper reference | 500 mcg (0.5 mg) | 0.1 mL | 10 units | 10 units |
Calculation basis: The table uses the labelled 10 mg amount and assumes a final solution volume of 2 mL (5 mg/mL). BAC volume does not change the amount of peptide. These are nominal calculations, not validation of preparation, compatibility or treatment.
Frequency: Once daily. For gut-focused use some protocols split 250 mcg every 12 hours.
Cycle: 4–8 weeks on, then 2–4 weeks off.
Reconstitution Steps
- Allow the vial to reach room temperature before opening to minimize condensation.
- Draw 2 mL bacteriostatic water with a sterile syringe.
- Inject slowly down the vial wall to minimize foaming; avoid shaking.
- Gently swirl or roll the vial until the powder is fully dissolved.
- Label the vial with the reconstitution date and refrigerate at 2–8 °C (35.6–46.4 °F), protected from light.
- Use reconstituted solution within 28 days for maximum potency and safety.
Important: This guide is for educational purposes only and is not medical advice. For research use only. Not for human consumption.
Supplies Needed
Plan based on a 4–8 week once-daily protocol at the 300 mcg working dose.
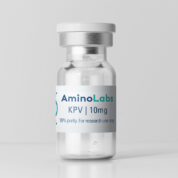
- Peptide Vials (KPV, 10 mg each):
- 4 weeks ≈ 1 vial (8.4 mg total used)
- 8 weeks ≈ 2 vials (16.8 mg total used)
- Insulin Syringes (U-100):
- Per week: 7 syringes
- 4 weeks: 28 syringes
- 8 weeks: 56 syringes
- Bacteriostatic Water (30 mL bottles): Use 2 mL per vial for reconstitution.
- 4 weeks (1 vial): 2 mL → 1 × 30 mL bottle
- 8 weeks (2 vials): 4 mL → 1 × 30 mL bottle
Note: Use bacteriostatic water within 28 days after opening; a vial reconstituted more than 28 days after the bottle was first opened needs a new bottle.
- Alcohol Swabs: One for the vial stopper + one for the injection site each injection.
- 4 weeks: 56 swabs → recommend 1 × 100-count box
- 8 weeks: 112 swabs → recommend 2 × 100-count boxes
Protocol Overview
Concise summary of the once-daily anti-inflammatory regimen.
- Goal: Reduce gut and systemic inflammatory signaling through NF-kB inhibition without activating the pigmentation pathway of alpha-MSH.
- Schedule: Daily subcutaneous injections for 4–8 weeks, followed by a 2–4 week break before any repeat cycle.
- Dose Range: 200 mcg (0.2 mg) to 500 mcg (0.5 mg) once daily, with 300 mcg (0.3 mg) as the standard working dose from week 3.
- Reconstitution: 2 mL per 10 mg vial (5 mg/mL) for accurate unit measurements on standard insulin syringes.
- Storage: Lyophilized frozen at −20 °C (−4 °F); reconstituted refrigerated at 2–8 °C (35.6–46.4 °F); use within 28 days; avoid repeated freeze–thaw cycles.
- Evidence: Animal data only (mouse DSS and TNBS colitis models, Dalmasso 2008 and Kannengiesser 2008) plus cell studies; no completed human RCT, and the single human case on a pharmacy site is anecdotal. The 200–500 mcg once-daily convention and the 10 mg + 2 mL reconstitution are consistent across sources, so confidence in the convention is medium, but every source labels the figures community-derived.
Dosing Protocol
Suggested daily approach based on preclinical data and research-community conventions.
- Weeks 1–2: 200 mcg (0.2 mg) once daily to establish tolerance; 4 units at the 5 mg/mL reconstitution.
- Week 3 onward: 300 mcg (0.3 mg) once daily as the standard working dose; 6 units.
- Upper reference: 500 mcg (0.5 mg) once daily; 10 units. This is the top of the range shared by four of five sources, not a target.
- Frequency: Once daily, subcutaneously. For gut-focused use some protocols split the day into 250 mcg every 12 hours (5 units per injection).
- Timing: No time-of-day convention exists for the subcutaneous route; keep the injection at a consistent time and rotate sites.
- Cycle: 4–8 weeks on, then 2–4 weeks off. Sources describe 4–12 weeks for acute phases and 8–12 weeks for gut-focused oral protocols.
- Maintenance: One source describes tapering from daily to three times weekly after an acute phase; most sources simply stop at the end of the cycle and reassess.
Storage Instructions
Proper storage preserves product quality and efficacy.
- Lyophilized (powder): Store frozen at −20 °C (−4 °F) for long-term storage, or refrigerated at 2–8 °C (35.6–46.4 °F) for short periods, dry and protected from light; sources describe 12 months or more of stability unreconstituted.
- Reconstituted (solution): Refrigerate at 2–8 °C (35.6–46.4 °F) and do not freeze. Use within 28 days and avoid temperature cycling.
- Allow the vial to reach room temperature before opening to minimize condensation uptake.
- Inject the bacteriostatic water against the vial wall and never shake; the tripeptide dissolves readily with gentle swirling.
Important Notes
Practical considerations for consistency and safety.
- Use new sterile insulin syringes for each injection; dispose in a proper sharps container.
- Rotate injection sites systematically (abdomen, thighs, upper arms) to reduce local irritation and avoid lipohypertrophy.
- Route note: the Amino Labs product is injectable. Sources prefer the oral route (enteric or delayed-release capsules at 200–500 mcg per day, up to 500–1000 mcg for gut-focused use) for intestinal goals because KPV is taken up by the PepT1 transporter in inflamed gut tissue, and the subcutaneous route for systemic goals. Oral and topical figures are context only and do not apply to this vial.
- Not approved by Health Canada or the FDA; research use only. An FDA compounding review noted that no human exposure data were identified.
- Evidence caveat: all efficacy data come from mouse colitis and cell models. No completed human RCT exists, and every source labels the 200–500 mcg figures as community-reported practice rather than clinically established dosing.
- KPV does not activate the MC1R pigmentation pathway, so no tanning is expected; this distinguishes it from full alpha-MSH and from Melanotan analogues.
- Sources describe onset of 1–2 weeks for the subcutaneous route; a cycle shorter than four weeks gives little basis for assessing the response.
- KPV is often stacked with BPC-157 for gut protocols and is one of the four components of the KLOW blend; if a KLOW cycle is running, a separate KPV injection duplicates that component.
How This Works
KPV is the three-amino-acid C-terminal fragment (lysine-proline-valine) of alpha-melanocyte-stimulating hormone. The full hormone has broad anti-inflammatory effects but also drives pigmentation through the MC1R receptor; the KPV fragment keeps the anti-inflammatory activity and leaves the pigmentation pathway untouched. In cell and animal studies, KPV is carried into cells, particularly inflamed intestinal epithelium, by the PepT1 peptide transporter, which is upregulated during gut inflammation. Once inside, it blocks nuclear translocation of the NF-kB p65 subunit, inhibits the NLRP3 inflammasome and MAPK signaling, and shifts macrophages from the pro-inflammatory M1 state toward the anti-inflammatory M2 phenotype. The net effect is a reduction in pro-inflammatory cytokine production at the site of inflammation. Mouse colitis models (DSS and TNBS, 2008) showed reduced intestinal inflammation with KPV, and in vitro work has reported antimicrobial activity. No human trial has been completed, so the human dose, onset and durability of these effects remain uncharacterized.
Potential Benefits & Side Effects
Observations from preclinical literature and research-community reporting.
Potential Benefits:
- Reduced intestinal inflammation in mouse DSS and TNBS colitis models, the main evidence base for gut-focused use.
- Systemic inflammation reduction through NF-kB and NLRP3 inhibition, shown in cell and animal studies.
- Skin inflammation support (eczema, psoriasis, wound models) with topical formulations; context only for this injectable product.
- Mast-cell and allergic symptom modulation with intranasal use, the least-studied application.
- Antimicrobial activity in vitro.
- One anecdotal case report on a pharmacy site describes a fall in faecal calprotectin on oral KPV; it is a single uncontrolled observation.
Potential Side Effects:
- Mild, transient injection-site redness or irritation is the most commonly reported effect.
- GI discomfort, mainly with the oral route.
- Fatigue and headache, both uncommon.
- Nasal or local skin irritation with intranasal or topical use (other routes, for context).
- No tanning or immunosuppression; KPV does not activate the MC1R pigmentation pathway.
- No human safety trial has been completed, so the adverse-effect profile is based on community reports.
Lifestyle Factors
Complementary strategies for an anti-inflammatory protocol.
- Follow an anti-inflammatory dietary pattern with fiber, vegetables and omega-3 sources, and limit ultra-processed foods and alcohol, which aggravate gut inflammation.
- Identify and reduce individual dietary triggers with a food and symptom diary, since inflammatory gut symptoms often track specific foods.
- Prioritize 7–9 hours of sleep; short sleep raises circulating inflammatory markers.
- Use regular moderate exercise, which lowers baseline inflammation, while avoiding heavy exertion during a symptomatic flare.
- Manage stress with a consistent practice such as breathing exercises or mindfulness; the gut-brain axis links stress to intestinal inflammation.
- Track symptoms week by week so that the response over a 4–8 week cycle can be assessed on recorded data.
Injection Technique
General subcutaneous injection guidance from clinical best-practice resources.
- Clean the vial stopper and chosen skin site with separate alcohol swabs; allow both to dry completely before proceeding.
- Pinch a fold of skin between your fingers; insert the needle at a 45–90° angle into the subcutaneous tissue (fatty layer, not muscle).
- Do not aspirate (pull back the plunger) when giving a subcutaneous injection.
- Inject the solution slowly and steadily; wait at least 6 seconds after injection before withdrawing the needle to ensure complete delivery and minimize leakage.
- Withdraw the needle and apply light pressure with a clean swab; avoid rubbing vigorously.
- Rotate injection sites systematically (abdomen, thighs, upper arms) to prevent lipohypertrophy and maintain consistent absorption.
- Dispose of used syringes and needles immediately in a proper sharps container.
Recommended Source
We recommend Amino Labs for high-purity KPV (10 mg vials).
Why Amino Labs?
- Third-party tested: Each batch includes Certificate of Analysis (COA) verifying purity and composition.
- Consistent quality: ISO-aligned manufacturing and handling standards ensure reliable product integrity.
- Cold-chain integrity: Temperature-controlled shipping and storage throughout fulfillment process.
- Research-grade purity: Suitable for educational and research applications requiring high-quality peptides.
Note: Product availability and specifications subject to change. Verify current product details on supplier website.
Important Note
This content is intended for therapeutic educational purposes only and does not constitute medical advice, diagnosis, or treatment.