
Quickstart Highlights
TB-500 is a synthetic fragment of thymosin beta-4 containing the protein’s actin-binding domain, studied for soft-tissue, tendon and ligament repair, angiogenesis and reduced inflammation in animal models of wound and cardiac injury. No human trial of injectable TB-500 exists; human data cover only full-length thymosin beta-4. This educational protocol presents the research-community loading-then-maintenance structure: 2 mg (2.5 mg upper) twice weekly for the first 4 weeks, then 2 mg (2.5 mg upper) once weekly through week 12, followed by 4–8 weeks off, using a 2.0 mL reconstitution (5 mg/mL) so each injection is a whole number of units on a U-100 insulin syringe.
- Reconstitute: Add 2 mL bacteriostatic water → 5 mg/mL concentration.
- Dose range: 2–2.5 mg per injection, subcutaneously: twice weekly during loading (weeks 1–4), then once weekly for maintenance (8–12 week course, then 4–8 weeks off).
- Easy measuring: At 5 mg/mL, 1 unit = 0.01 mL = 50 mcg on a U-100 insulin syringe.
- Storage: Lyophilized: freeze at −20 °C (−4 °F); after reconstitution, refrigerate at 2–8 °C (35.6–46.4 °F) and use within 28 days.
- Label: Not approved anywhere and prohibited by WADA (detection window 30–45 days); the loading and maintenance figures are community convention with animal data only.

Dosing & Reconstitution Guide
Loading and Maintenance Protocol (2 mL = 5 mg/mL)
| Phase | Dose | Calculated volume | U-100 scale value (1 mL capacity) | V1 nominal setting (units) |
|---|---|---|---|---|
| Weeks 1–4 (loading, twice weekly) | 2 mg (2000 mcg) | 0.4 mL | 40 units | 40 units |
| Weeks 1–4 (loading, upper) | 2.5 mg (2500 mcg) | 0.5 mL | 50 units | 50 units |
| Weeks 5–12 (maintenance, once weekly) | 2 mg (2000 mcg) | 0.4 mL | 40 units | 40 units |
| Maintenance upper | 2.5 mg (2500 mcg) | 0.5 mL | 50 units | 50 units |
Calculation basis: The table uses the labelled 10 mg amount and assumes a final solution volume of 2 mL (5 mg/mL). BAC volume does not change the amount of peptide. These are nominal calculations, not validation of preparation, compatibility or treatment.
Frequency: Twice weekly during the 4-week loading phase (4–5 mg/week; some sources extend loading to 6 weeks), then once weekly for maintenance through week 12 (some sources stretch maintenance to once every two weeks). Not time-of-day sensitive.
Cycle: 8–12 weeks total, then 4–8 weeks off.
Reconstitution Steps
- Allow the vial to reach room temperature before opening to minimize condensation.
- Draw 2 mL bacteriostatic water with a sterile syringe.
- Inject slowly down the vial wall to minimize foaming; avoid shaking.
- Gently swirl or roll the vial until the powder is fully dissolved.
- Label the vial with the reconstitution date and refrigerate at 2–8 °C (35.6–46.4 °F), protected from light.
- Use reconstituted solution within 28 days for maximum potency and safety.
Important: This guide is for educational purposes only and is not medical advice. For research use only. Not for human consumption.
Supplies Needed
Plan based on a 4–12 week course: twice-weekly loading for weeks 1–4, then once-weekly maintenance at the 2 mg dose.
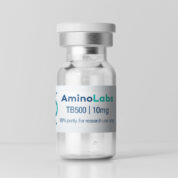
- Peptide Vials (TB-500, 10 mg each):
- 4 weeks ≈ 2 vials (16 mg total used)
- 8 weeks ≈ 3 vials (24 mg total used)
- 12 weeks ≈ 4 vials (32 mg total used)
- Insulin Syringes (U-100):
- Per week: 2 syringes during loading (weeks 1–4), 1 during maintenance
- 4 weeks: 8 syringes
- 8 weeks: 12 syringes
- 12 weeks: 16 syringes
- Bacteriostatic Water (30 mL bottles): Use 2 mL per vial for reconstitution.
- 4 weeks (2 vials): 4 mL → 1 × 30 mL bottle
- 8 weeks (3 vials): 6 mL → 2 × 30 mL bottles
- 12 weeks (4 vials): 8 mL → 3 × 30 mL bottles
Note: Use bacteriostatic water within 28 days after opening; a vial reconstituted more than 28 days after the bottle was first opened needs a new bottle.
- Alcohol Swabs: One for the vial stopper + one for the injection site each injection.
- 4 weeks: 16 swabs
- 8 weeks: 24 swabs
- 12 weeks: 32 swabs
Protocol Overview
Concise summary of the loading-then-maintenance regimen.
- Goal: Support soft-tissue, tendon and ligament repair, angiogenesis and reduced inflammation through the actin-binding and cell-migration effects observed in animal models.
- Schedule: Subcutaneous injections twice weekly for the 4-week loading phase, then once weekly for maintenance through week 12; 8–12 weeks total followed by 4–8 weeks off.
- Dose Range: 2000 mcg (2 mg) to 2500 mcg (2.5 mg) per injection: 4–5 mg per week during loading and 2–2.5 mg per week during maintenance.
- Reconstitution: 2 mL per 10 mg vial (5 mg/mL) for accurate unit measurements on standard insulin syringes.
- Storage: Lyophilized frozen at −20 °C (−4 °F); reconstituted refrigerated at 2–8 °C (35.6–46.4 °F); use within 28 days; avoid repeated freeze–thaw cycles.
- Evidence: Animal data only for the TB-500 fragment; the loading-then-maintenance structure is consistent across most sources but is entirely convention with no human dose data, so confidence is medium.
Dosing Protocol
Suggested loading and maintenance approach based on preclinical data and research-community conventions.
- Weeks 1–4 (loading, twice weekly): 2000 mcg (2 mg) per injection, twice weekly (4 mg per week).
- Weeks 1–4 (loading, upper): 2500 mcg (2.5 mg) per injection, twice weekly (5 mg per week), the upper loading reference.
- Weeks 5–12 (maintenance, once weekly): 2000 mcg (2 mg) once weekly.
- Maintenance upper: 2500 mcg (2.5 mg) once weekly.
- Frequency: Twice weekly, evenly spaced, during the 4-week loading phase (4–5 mg per week; some sources extend loading to 6 weeks), then once weekly for maintenance (some sources stretch this to once every two weeks).
- Timing: Not time-of-day sensitive; sources describe injecting at any consistent time with no fasting requirement.
- Cycle: 8–12 weeks total (loading plus maintenance), then 4–8 weeks off; a shorter alternative uses the 4–6 week loading phase only.
- Maintenance: Some sources extend the maintenance interval to one injection every 2 weeks or every 10–14 days once the loading phase is complete.
Storage Instructions
Proper storage preserves product quality and efficacy.
- Lyophilized (powder): Store at −20 °C (−4 °F) in a cool, dry place protected from light; 2–8 °C (35.6–46.4 °F) refrigeration is acceptable for short-term storage.
- Reconstituted (solution): Refrigerate at 2–8 °C (35.6–46.4 °F) and do not freeze. Use within 28 days; one outlier source states 7–10 days, but the consensus is 28–30 days.
- Allow vials to reach room temperature before opening to minimize condensation uptake.
- Never shake after reconstitution; swirl or roll the vial gently until the powder dissolves.
Important Notes
Practical considerations for consistency and safety.
- Use new sterile insulin syringes for each injection; dispose in a proper sharps container.
- Rotate injection sites systematically (abdomen, thighs, upper arms) to reduce local irritation and avoid lipohypertrophy. Sources describe subcutaneous injection as the primary route; some describe intramuscular injection near an injury as an alternative, which uses a different needle.
- Inject slowly and steadily; wait a few seconds before withdrawing the needle to ensure complete delivery. At 5 mg/mL a 2 mg injection is 40 units (0.4 mL) and 2.5 mg is 50 units (0.5 mL), both within a single 1 mL syringe and under the V1 pen’s 80-unit cap.
- Regulatory: Not approved by Health Canada or the FDA; research use only. TB-500 is prohibited by WADA (S0 category) with a reported detection window of 30–45 days, which matters for any tested athlete.
- Evidence caveat: Animal data only (rodent and equine wound, cardiac and corneal models) for the fragment; the closest human data are a Phase 1 intravenous safety study of full-length thymosin beta-4 and Phase 2 wound and corneal studies. No published human RCT of injectable TB-500 exists.
- Vial planning: A 10 mg vial yields 5 injections at 2 mg (4 at 2.5 mg), so reconstitute one vial at a time to stay within the 28-day window; the Supplies section gives vial counts per course length.
- Angiogenesis concern: Because TB-500 promotes new blood-vessel formation, sources list active cancer as a contraindication on theoretical grounds.
- Commonly stacked with BPC-157 by community convention (matched daily micro-dosing or in KLOW/GLOW blends); that daily pattern is a minority convention distinct from the weekly loading-and-maintenance schedule on this page.
How This Works
TB-500 is a synthetic peptide corresponding to the actin-binding region of thymosin beta-4 (the Ac-LKKTETQ segment), a protein that regulates the pool of free G-actin inside cells. By sequestering G-actin, TB-500 alters cytoskeletal dynamics in a way that promotes cell migration: endothelial cells, keratinocytes and progenitor cells move more readily toward sites of injury, which supports new blood-vessel formation and faster wound closure. It also down-regulates inflammatory signaling through the ILK and BMP-4 pathways, reducing stiffness and swelling in injured tissue. Together these actions accelerate tissue remodelling in rodent and equine models of wound, tendon, corneal and cardiac injury. The loading-then-maintenance schedule is a community convention that front-loads exposure in the first weeks and then sustains it; it has not been tested in a human trial, and a Phase 1 intravenous study of full-length thymosin beta-4 that found no dose-limiting toxicity does not translate directly to subcutaneous dosing of the fragment.
Potential Benefits & Side Effects
Observations from animal models and the full-length thymosin beta-4 literature.
Potential Benefits:
- Accelerated soft-tissue, tendon and ligament repair in animal models.
- Angiogenesis and improved blood flow to injured tissue (animal data).
- Reduced inflammation and stiffness; improved mobility reported within 7–14 days in community sources, with measurable change by weeks 4–6.
- Stem and progenitor cell migration and recruitment to injury sites (animal data).
- Cardiac and wound healing in animal models of full-length thymosin beta-4; human Phase 2 data exist only for the full-length protein in wound and corneal healing.
Potential Side Effects:
- Transient fatigue or lethargy, the most commonly reported effect.
- Mild headache.
- Injection-site redness, discomfort or bruising.
- Blood-pressure fluctuation; rare nausea reported at 6 mg per week or above.
- Water retention when stacked with GH secretagogues.
- Theoretical angiogenesis and tumor-growth concern; active cancer is listed as a contraindication. WADA-prohibited with a 30–45 day detection window.
Lifestyle Factors
Complementary strategies for tissue repair and recovery.
- Follow a structured rehabilitation or progressive loading plan for the injured tissue; peptide exposure does not replace graded mechanical stimulus.
- Maintain adequate protein intake (1.2–1.6 g/kg body weight) and overall energy to supply the building blocks for tissue remodelling.
- Prioritize 7–9 hours of sleep, when most tissue repair occurs.
- Avoid smoking and routine NSAID use where possible, both of which impair tendon and ligament healing.
- Stay hydrated and keep the weekly amount within the reference range rather than escalating; nausea is reported at higher weekly totals.
- Record pain, range of motion and function weekly to judge the 7–14 day and 4–6 week milestones sources describe.
Injection Technique
General subcutaneous injection guidance from clinical best-practice resources.
- Clean the vial stopper and chosen skin site with separate alcohol swabs; allow both to dry completely before proceeding.
- Pinch a fold of skin between your fingers; insert the needle at a 45–90° angle into the subcutaneous tissue (fatty layer, not muscle).
- Do not aspirate (pull back the plunger) when giving a subcutaneous injection.
- Inject the solution slowly and steadily; wait at least 6 seconds after injection before withdrawing the needle to ensure complete delivery and minimize leakage.
- Withdraw the needle and apply light pressure with a clean swab; avoid rubbing vigorously.
- Rotate injection sites systematically (abdomen, thighs, upper arms) to prevent lipohypertrophy and maintain consistent absorption.
- Dispose of used syringes and needles immediately in a proper sharps container.
Recommended Source
We recommend Amino Labs for high-purity TB-500 (10 mg vials).
Why Amino Labs?
- Third-party tested: Each batch includes Certificate of Analysis (COA) verifying purity and composition.
- Consistent quality: ISO-aligned manufacturing and handling standards ensure reliable product integrity.
- Cold-chain integrity: Temperature-controlled shipping and storage throughout fulfillment process.
- Research-grade purity: Suitable for educational and research applications requiring high-quality peptides.
Note: Product availability and specifications subject to change. Verify current product details on supplier website.
Important Note
This content is intended for therapeutic educational purposes only and does not constitute medical advice, diagnosis, or treatment.